
Referrals
Dentists please fill out the referral form below - if you are a patient, please get in touch with your regular dentist to initiate the referral process.
Alastair MacDonald
Alastair is a graduate from Glasgow University (BDS, 1985) and a Masters from Indiana University (MSD, 1992).
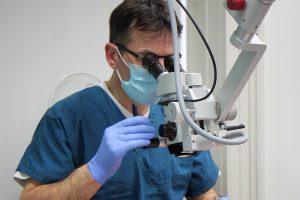
Endodontics
Learn more about the techniques and technology used in Endodontics and the process of treating root canals.

Referrals
Patients must be referred from their regular dentist. Dentists can fill out a referral form here.

Patient Care
Read about how best to prepare for your root canal treatment, and care for it after the procedure.